Integrating Human Biology with the Internet of Things
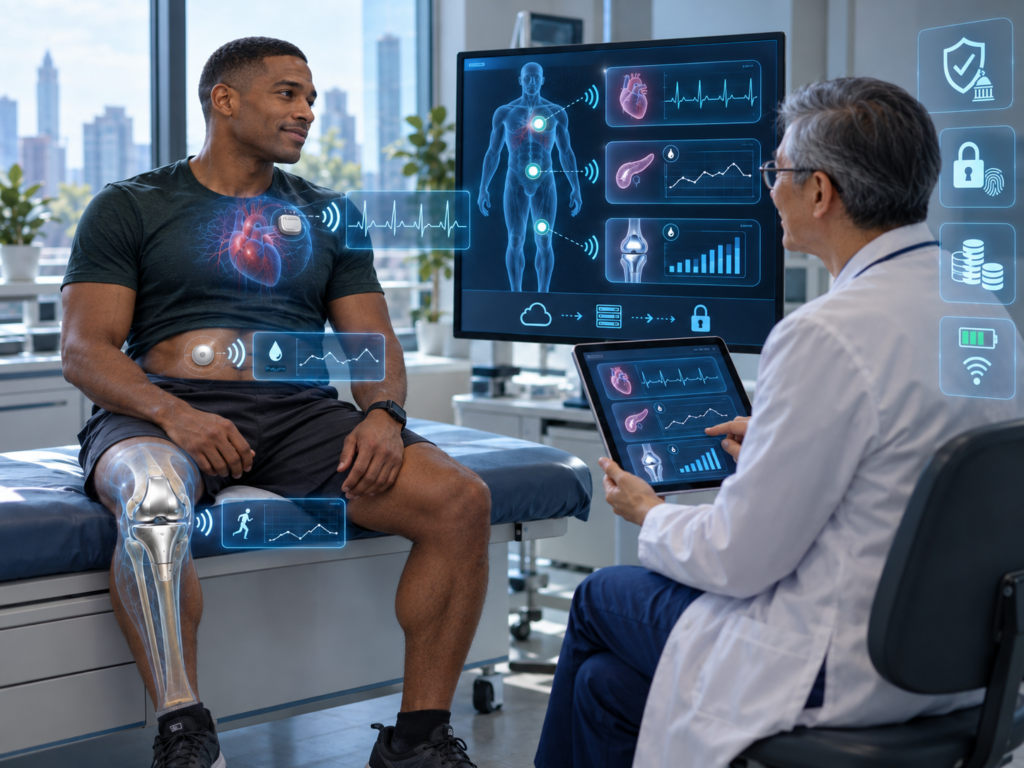
The integration of human biology with Internet of Things (IoT) technology is often referred to as “bio-IoT” or “biomedical IoT.” This concept involves the convergence of biological sensors, medical devices, and wearable technologies with IoT infrastructure to monitor, analyze, and manage various aspects of human health and well-being continuously or periodically, including in near real-time where applicable.
Bio-IoT systems typically involve the use of sensors and devices capable of capturing physiological data such as heart rate, blood pressure, temperature, glucose levels, and activity levels. These devices may be wearable or implantable and can be connected to IoT networks, allowing for ongoing or periodic data collection and transmission to relevant platforms for analysis.
The integration of human biology with IoT technology enables a wide range of applications in healthcare, including remote patient monitoring, personalized medicine, disease management, and preventive care. It can help healthcare providers monitor patients’ health status more effectively, identify potential early warning signs of health problems, and support appropriate intervention.
Overall, bio-IoT represents an area at the intersection of healthcare and technology, with the potential to significantly expand and change how aspects of human health are monitored and managed in the digital age.
Selected Research and Technical Literature
The following studies provide examples of research relevant to the intersection of IoT technologies, healthcare, biological sensing, bio-cyber interfaces, and emerging Internet of Bio-Nano Things (IoBNT) concepts. Together, they illustrate both established healthcare-IoT applications and more exploratory approaches involving increasingly integrated biological and technological systems.
Edge Intelligence and Internet of Things in Healthcare: A Survey
Amin, S. U., & Hossain, M. S. (2021). This study examines smart healthcare frameworks that combine IoT sensors, 5G connectivity, edge computing, and artificial intelligence. It discusses applications involving health-data processing, classification, vital-sign monitoring, and increasingly responsive healthcare systems.
Read the articleThe Internet of Bio-Nano Things
Akyildiz, I. F., Pierobon, M., Balasubramaniam, S., & Koucheryavy, Y. (2015). This paper introduces the concept of the Internet of Bio-Nano Things (IoBNT), which explores the interconnection of nanoscale devices and biological components. The proposed framework considers possible applications involving intra-body sensing, biological communication, and other forms of interaction between biological and engineered systems.
Read the articlePANACEA: An Internet of Bio-NanoThings Application for Early Detection and Mitigation of Infectious Diseases
Akyildiz, I. F., Ghovanloo, M., Guler, U., Ozkaya-Ahmadov, T., Sarioglu, A. F., & Unluturk, B. D. (2020). This study presents PANACEA, a proposed IoBNT application focused on infectious-disease detection and response. The system combines sensing, actuation, communication, and computational processes to explore how bio-nano networks might support disease monitoring and responsive healthcare applications.
Read the article
Author-hosted full PDFIoT Middleware: A Survey on Issues and Enabling Technologies
Ngu, A. H., Gutierrez, M., Metsis, V., Nepal, S., & Sheng, Q. Z. (2017). This paper surveys middleware architectures and enabling technologies used within IoT systems. Although broader than biomedical IoT alone, it provides relevant background on the intermediary software and infrastructure that allow connected devices, applications, and data-processing systems to communicate and operate together, including within healthcare-related environments.
Read the articleA Systematic Review of Bio-Cyber Interface Technologies and Security Issues for Internet of Bio-Nano Things
Zafar, S., Nazir, M., Bakhshi, T., Khattak, H. A., Khan, S., Bilal, M., Choo, K.-K. R., Kwak, K.-S., & Sabah, A. (2021). This review examines bio-cyber interface technologies relevant to IoBNT and discusses technical challenges associated with connecting biological and cyber systems. It also highlights important considerations involving security, privacy, communication, and the reliability of increasingly integrated biological and digital technologies.
Read the article
Free arXiv version
These sources illustrate research across healthcare IoT, biological sensing, bio-nano communications, bio-cyber interfaces, and supporting IoT infrastructure. They highlight potential applications in monitoring, disease management, sensing, data analysis, and responsive healthcare systems while also identifying technical, security, privacy, and implementation challenges associated with increasingly integrated biological and digital technologies.
The maturity of these technologies varies. Some healthcare-IoT applications are already established or actively deployed, while other concepts—particularly those involving bio-nano networks and deeply integrated biological interfaces—remain more exploratory or developmental. Accordingly, these studies are best understood as examples of the range of research occurring across this evolving field rather than as evidence that all described technologies are presently mature or widely implemented.
Commonly Implemented Bio-IoT Devices

The adoption of IoT-related and connected monitoring capabilities in medical implants varies significantly depending on the type of implant, its intended function, technological maturity, clinical need, supporting infrastructure, and regulatory environment.
In many cases, the implanted device does not connect directly to the internet. Instead, it may communicate wirelessly with an external transmitter, base station, smartphone, or other intermediary device that then connects to a network or remote monitoring platform.
Types of Medical Implants with Connected Capabilities
Cardiac Devices: Some of the most established uses of connected monitoring in medical implants are found in cardiac care. Devices such as pacemakers and implantable cardioverter-defibrillators (ICDs) may include remote monitoring capabilities that allow healthcare providers to review information concerning heart rhythm, device status, and other relevant parameters without requiring every evaluation to occur in person.
Glucose Monitoring Systems: Some implantable continuous glucose monitoring systems can measure glucose levels through an implanted sensor and transmit data wirelessly to an external transmitter, mobile device, or associated monitoring platform. These systems can support frequent glucose monitoring and provide information that may assist patients and healthcare providers in diabetes management.
Orthopedic Implants: Sensor-enabled orthopedic implants represent an emerging area of connected medical technology. Some systems can collect information concerning characteristics such as movement, gait, range of motion, implant performance, or recovery-related activity and communicate that information through supporting external infrastructure. Although such technologies are already available in some applications, connected sensing is not yet standard across orthopedic implants as a whole.
Factors Influencing Adoption in Medical Implants
Regulatory Approval: Implantable medical devices are subject to significant regulatory review because they may directly affect patient health and safety. Adding wireless communication, software, remote monitoring, cybersecurity features, or other connected capabilities can increase the complexity of development, validation, approval, and post-market oversight.
Security and Privacy: Connected medical implants and their supporting systems can introduce cybersecurity and privacy concerns. Protecting device operation, communications, patient information, authentication, software, and associated infrastructure is therefore an important part of system design and risk management.
Cost and Accessibility: Developing, manufacturing, maintaining, and supporting connected implantable technologies can involve substantial cost. Infrastructure requirements, specialized clinical support, insurance coverage, regional availability, and healthcare-system resources may also affect accessibility and adoption.
Technological Challenges: Connected implants may require reliable sensing, wireless communication, power management, data processing, interoperability, software support, and compatibility with existing healthcare infrastructure. Depending on the system, battery life, signal reliability, calibration, data quality, maintenance, and long-term durability may also present important engineering challenges.
Clinical Need and Benefit: Not every implant requires continuous sensing or remote connectivity. The value of adding connected capabilities depends upon whether they provide a meaningful clinical, operational, or monitoring benefit relative to the added complexity, cost, risk, and Resource requirements.
In summary, the integration of connected sensing, wireless communication, and remote-monitoring capabilities into medical implants offers significant potential for improving patient monitoring, supporting earlier recognition of relevant changes, and enabling more individualized care.
However, widespread adoption across implantable medical devices as a whole is not yet a reality. The pace and extent of integration remain influenced by technological maturity, clinical need, regulatory requirements, cybersecurity and privacy considerations, cost, accessibility, infrastructure, and other ethical and practical considerations.
Connected capability should therefore be evaluated according to the particular medical application rather than treated as an inherently necessary or superior feature of every implantable device.
Pacemakers have evolved significantly since their introduction, incorporating increasingly advanced technologies to improve monitoring, device management, and patient care. Some modern pacemakers now include connected or remote-monitoring capabilities that allow device and cardiac data to be transmitted to healthcare providers through supporting external systems.
In many cases, the pacemaker itself does not connect directly to the internet. Instead, it may communicate wirelessly with a smartphone, bedside communicator, or other external device that then transmits relevant information to a clinical monitoring platform.
This can allow healthcare professionals to review device status and cardiac information remotely, potentially reducing the need for some routine in-person device checks and supporting more timely clinical follow-up when relevant changes are detected.
Key Benefits of Connected or Remotely Monitored Pacemakers
Remote Monitoring: Connected pacemaker systems can allow relevant device and cardiac data to be transmitted remotely for periodic or automatic clinical review. This may include information concerning heart rhythm, device performance, battery status, or other parameters supported by the particular system.
Earlier Recognition of Relevant Changes: Remote monitoring may help identify clinically relevant changes, device issues, abnormal rhythms, or other conditions earlier than might otherwise occur, supporting appropriate clinical evaluation and follow-up.
Greater Convenience for Some Patients: Remote monitoring can reduce the need for some routine in-person device checks. This may be particularly useful for patients who live far from specialized care, have mobility limitations, or otherwise face barriers to frequent clinic visits.
Support for More Individualized Care: Data collected through remote-monitoring systems can provide healthcare professionals with additional information about the patient and implanted device over time. When appropriately interpreted within the clinical context, this information may support more individualized monitoring and management decisions.
Potential to Support Improved Patient Outcomes: By supporting earlier recognition of relevant changes, improved follow-up, and more individualized care, connected pacemaker systems may contribute to better clinical management and patient quality of life. The extent of benefit depends upon the patient, device, monitoring system, clinical response, and other relevant conditions.
Considerations and Challenges
Security and Privacy: Connected medical-device systems can introduce cybersecurity and privacy risks. Protecting device communications, patient information, authentication systems, software, and associated infrastructure is therefore an important part of design, operation, and risk management.
Regulatory and Ethical Considerations: Remote-monitoring technologies must operate within applicable medical-device regulations, clinical standards, privacy requirements, informed-consent practices where applicable, and other legal and ethical obligations.
Technology Access and Usability: Remote-monitoring systems may require compatible smartphones or communicators, cellular or internet connectivity, digital familiarity, technical support, or caregiver assistance. These requirements can create practical barriers for some patients regardless of age.
Clinical Interpretation and Follow-Up: Remote data does not eliminate the need for professional medical judgment. Alerts, measurements, and device information must be interpreted within the broader clinical context, and remote monitoring does not guarantee that every problem will be detected immediately.
In conclusion, while not all pacemakers use connected or remote-monitoring technology, these capabilities are increasingly incorporated into modern cardiac-device care. They can support remote review, earlier recognition of relevant changes, reduced reliance on some routine in-person checks, and more individualized clinical management.
However, their successful use depends upon appropriate clinical oversight, reliable technology, cybersecurity, privacy protection, regulatory compliance, patient access, and careful interpretation of the information being transmitted.
Additional Research and Technical Literature

The following publications illustrate important developments and research directions involving biointegrated electronics, healthcare IoT, biological sensing, tissue–electronics interfaces, connected biosensors, prosthetic technologies, and IoT security and privacy. Together, they provide additional context for understanding how increasingly connected technologies may interact with the human body and healthcare systems.
Flexible and Stretchable Electronics for Biointegrated Devices
Kim, D.-H., Ghaffari, R., Lu, N., & Rogers, J. A. (2012). This review examines advances in materials, mechanics, and manufacturing that allow electronic and optoelectronic systems to integrate with the soft, curved, and dynamic surfaces of the human body. Applications discussed include health monitoring, surgical technologies, human–machine interfaces, and devices designed to interface with areas such as the skin, heart, and brain.
Read the articleThe Internet of Things for Health Care: A Comprehensive Survey
Islam, S. M. R., Kwak, D., Kabir, M. H., Hossain, M., & Kwak, K. S. (2015). This survey reviews IoT-based healthcare technologies, including network architectures, platforms, applications, services, industry trends, and associated security and privacy considerations. It provides broader systems-level context for understanding how connected sensors, devices, communications infrastructure, and healthcare applications may operate together.
Read the articleTissue–Electronics Interfaces: From Implantable Devices to Engineered Tissues
Feiner, R., & Dvir, T. (2018). This review examines electronic technologies designed to interface directly with biological tissues. It discusses implantable devices, flexible and stretchable electronics, electrical stimulation, minimally invasive device integration, and approaches for obtaining physiological information from organs and tissues.
Read the articleA Megatrend Challenging Analytical Chemistry: Biosensor and Chemosensor Concepts Ready for the Internet of Things
Mayer, M., & Baeumner, A. J. (2019). This review examines the growing relationship between biosensors, chemical sensors, and IoT systems. It considers how connected sensing technologies may support applications involving health, environmental monitoring, agriculture, and other fields while identifying technical requirements and challenges associated with integrating analytical sensors into IoT architectures.
Read the articleTowards the sEMG Hand: Internet of Things Sensors and Haptic Feedback Application
Li, G., Zhang, L., Sun, Y., & Kong, J. (2019). This paper examines the integration of surface electromyography (sEMG), artificial sensory perception, tactile sensing, and haptic feedback in prosthetic-hand technologies. It considers how connected sensing and feedback systems may contribute to more capable prosthetic interfaces and improve the exchange of information between the device and its user.
Read the articleSecurity and Privacy Techniques in IoT Environment
Lin, J. C.-W., & Yeh, K.-H. (2020). This publication serves as an editorial introduction to research concerning security and privacy in IoT environments rather than as a standalone experimental healthcare study. It highlights the importance of protecting IoT ecosystems involving embedded systems, mobile devices, actuators, sensors, communications, and associated data. These concerns are particularly relevant when connected technologies process sensitive health or biological information.
Read the open-access article
These publications illustrate important research directions across biointegrated electronics, healthcare IoT, tissue–electronics interfaces, biosensing, prosthetic sensing and feedback, and cybersecurity.
Together, they demonstrate expanding technical possibilities for connecting biological sensing and medical technologies with digital systems while also highlighting significant challenges involving security, privacy, reliability, biocompatibility, data interpretation, clinical validation, system integration, and implementation.
The maturity of these technologies varies considerably. Some connected healthcare and sensing technologies are already established or clinically deployed, while other forms of deeply integrated biological–electronic interaction remain developmental or exploratory. These publications should therefore be understood as illustrating the breadth and progression of research in this field rather than establishing that all described technologies are presently mature, routinely available, or appropriate for every healthcare application.
Neural Networks, Biochips, & Human-IoT Integration
The question of whether neural networks or biochips are more likely to become common technologies for connecting human-generated biological or behavioral data with the Internet of Things (IoT) depends upon technological maturity, intended application, safety, privacy, regulation, clinical usefulness, accessibility, and the specific role each technology performs.
These technologies should not necessarily be understood as competitors. They perform substantially different functions and may increasingly operate together within larger systems.
Neural Networks
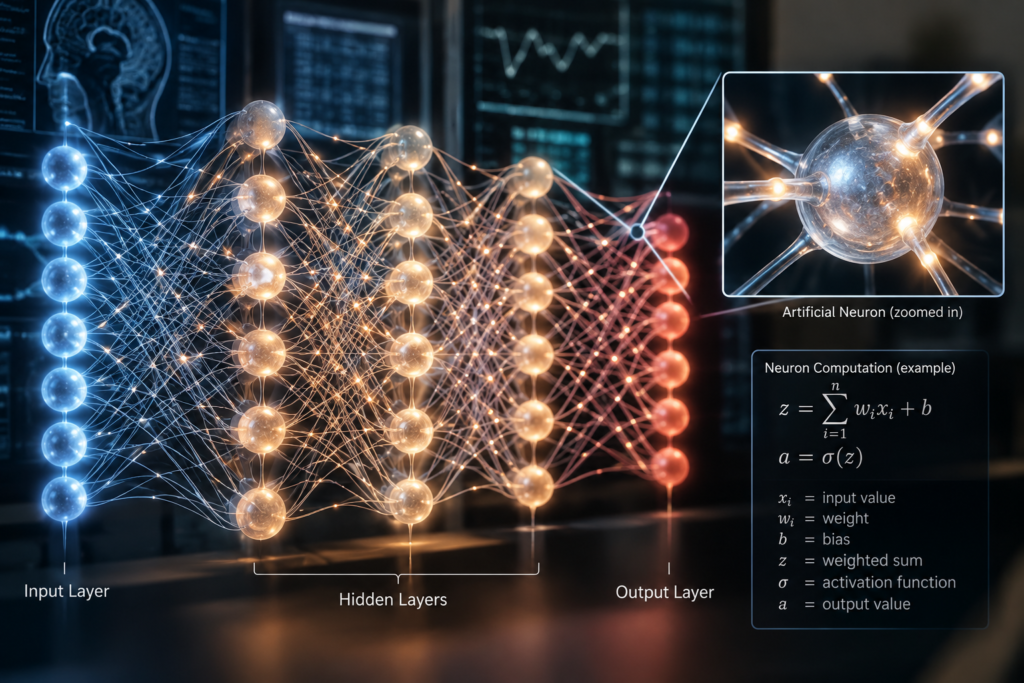
Definition: In this context, a neural network generally refers to an artificial neural network—a computational model designed to identify patterns, make classifications, generate predictions, or support other forms of data processing. Although artificial neural networks were historically inspired in part by biological nervous systems, they are engineered computational systems and should not be confused with the human brain or human intelligence itself.
Applications in IoT: Neural networks can analyze large quantities of data generated by connected sensors and devices. Within healthcare and human-centered IoT applications, they may assist with pattern recognition, anomaly detection, classification, forecasting, signal interpretation, and decision support.
Limitations and Strengths: Artificial neural networks generally do not provide the physical interface between the human body and an IoT system. Their primary role is computational: processing and interpreting data collected through sensors, medical devices, wearables, implants, or other Sources. Their usefulness depends upon factors such as data quality, model design, validation, transparency, security, appropriate human oversight, and suitability for the particular application.
Biochips and Biointegrated Devices
Definition: The term biochip can refer to several types of miniaturized devices used to detect, process, or interact with biological information. Depending upon the technology, a biochip may perform biochemical analysis, biological sensing, identification, monitoring, or other specialized functions.
Applications in IoT: In connected healthcare and biomedical systems, biochips or other biointegrated sensors may collect physiological or biochemical information and communicate that information through external devices or networked systems for monitoring, analysis, or appropriate clinical use.
Limitations and Strengths: Biochips and related technologies can operate close to or directly interface with biological systems, making them potentially useful for specialized medical, diagnostic, monitoring, or therapeutic applications. Their suitability depends upon factors such as safety, reliability, biocompatibility, clinical benefit, cybersecurity, privacy, informed participation where applicable, regulatory approval, long-term effects, and the proportionality of benefit to risk.
Biochips should therefore not be understood simply as technologies for making the human person part of an IoT network. More precisely, they can function as interfaces through which particular biological information or medically relevant functions may interact with larger technological systems.
Integration and Future Trends
Complementary Roles: Neural networks and biointegrated devices may increasingly function together. A sensor or biochip may collect relevant biological data, while artificial neural networks or other computational systems analyze that data for patterns, changes, or conditions that warrant further attention.
Conceptually:
Biological Condition → Sensor or Biointegrated Device → Data Transmission → Computational Analysis → Information or Decision Support → Appropriate Human or Clinical Response
This type of architecture could support applications such as remote monitoring, personalized healthcare, prosthetic control, assistive technologies, rehabilitation, disease management, or other legitimate uses.
Brain–Computer Interfaces: Some developing technologies seek to establish communication between neural activity and external computational systems. These systems may support medical or assistive applications, such as restoring communication or controlling external devices. Such technologies remain distinct from artificial neural networks themselves and should not be described as though software directly becomes part of human thought or identity.
Future Development: Research is advancing across artificial intelligence, biosensing, implantable devices, wearable electronics, prosthetics, and neural interfaces. However, technological capability alone does not determine whether a particular form of integration should become widespread.
Future adoption will also depend upon:
demonstrated safety and effectiveness;
meaningful benefit;
protection of privacy and personal information;
cybersecurity;
appropriate consent and user control;
accessibility;
reliability;
regulatory oversight;
reversibility where relevant;
protection against coercive or exploitative use;
and the effects of the technology upon the person and surrounding systems.
Human–Technology Integration Should Remain Purpose-Driven
The objective of human-centered IoT technology should not simply be to maximize technological integration.
Greater connectivity is not automatically better.
Greater data collection is not automatically beneficial.
Greater technological capability does not automatically justify its use.
The appropriate question is:
Does this technology provide a legitimate and proportionate benefit while respecting the person, protecting relevant rights and responsibilities, managing risks, and remaining appropriate to the actual need?
Technologies that interact closely with the human body should therefore be evaluated according to their purpose, necessity, safety, evidence, proportionality, privacy implications, security, long-term consequences, and effects upon human agency and well-being.
In Summary
Artificial neural networks and biochips are unlikely to represent two competing pathways in which one simply replaces the other.
Artificial neural networks principally provide computational analysis and interpretation, while biochips and related biointegrated devices may provide sensing or specialized interfaces with biological systems.
Future human-centered IoT architectures may combine these capabilities, particularly in healthcare, assistive technology, prosthetics, monitoring, and other specialized applications.
The most responsible direction is therefore not technological integration for its own sake, but the careful use of complementary technologies where they provide a demonstrable, proportionate, and appropriately governed benefit to the human person.
Piercing the Integration of Neural Networks & Biochips
Brain–Computer Interfaces: Connecting the Brain to Technology
Most people already understand the basic idea of using the body to control technology.
A person moves a finger, and a touchscreen responds.
A fitness watch senses a heartbeat and displays information on a phone.
A microphone detects a voice and converts it into commands.
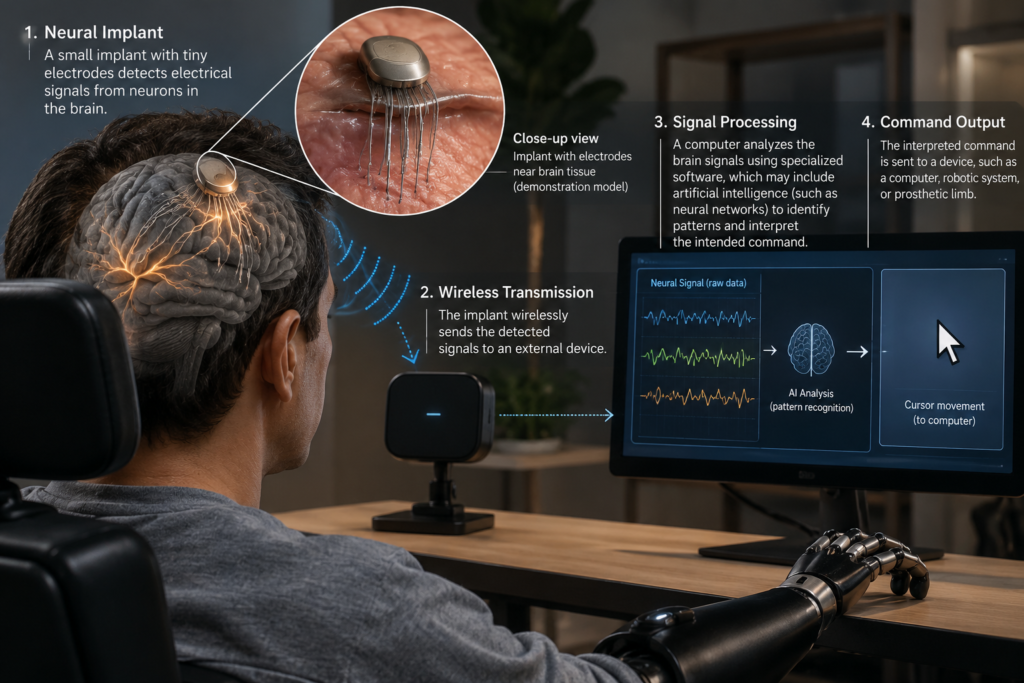
A brain–computer interface (BCI) takes this idea one step further by detecting signals associated with activity in the brain and using those signals to interact with a computer or another device.
In simple terms:
Brain Activity → BCI → Computer → Device Response
A BCI is therefore different from an artificial neural network.
An artificial neural network is software used to analyze information.
A BCI is the system that creates an interface between measurable brain activity and technology.
The two may work together, but they are not the same thing.
A Simple Example
Imagine a person who cannot move their hands but wants to move a computer cursor.
Normally, the person might:
Think About Moving → Move the Hand → Move the Mouse → Cursor Moves
With certain BCI systems, the physical hand movement may no longer be necessary.
Instead:
Think About an Intended Movement → Brain Activity Occurs → BCI Detects Relevant Signals → Computer Interprets Them → Cursor Moves
The computer is not necessarily reading the person’s entire mind.
It is detecting particular patterns of measurable brain activity that the system has been designed or trained to recognize.
This can allow a person to interact with technology even when ordinary physical movement is limited.
What Is Actually Implanted?
When people hear about companies developing technology that is implanted in the brain, they are usually hearing about an implantable brain–computer interface, not an artificial neural network itself.
The implanted portion may contain very small:
electrodes;
sensors;
electronic components;
signal-processing hardware;
and wireless communication technology.
These components detect certain electrical signals associated with neural activity.
The signals can then be sent to a computer or other device for interpretation.
Software—including artificial neural networks or other algorithms—may help determine what those signals mean within the specific system.
A helpful distinction is:
BCI = Detects or interacts with neural signals
Artificial Neural Network = Helps analyze information
Computer or Device = Performs the resulting action
Does This Connect the Brain to the Internet?
People sometimes describe BCIs as technology that “connects the brain to the internet.”
That description can be misleading if taken literally.
A more accurate pathway is:
Brain → BCI → Computer or Smartphone → Internet or Other Connected Device
The BCI communicates with a technological system.
That system may then connect to the internet.
This does not mean the internet suddenly has unlimited access to everything a person thinks, remembers, feels, or understands.
Current BCI systems are designed to detect particular types of measurable neural activity for specific purposes.
For example, a system might attempt to recognize neural signals associated with:
moving a cursor;
selecting a letter;
attempting a hand movement;
controlling a prosthetic device;
or producing another defined command.
That is very different from giving a computer complete access to someone’s mind.
BCIs Can Be Outside or Inside the Body
Not every BCI requires brain surgery.
Some systems use sensors placed on the outside of the head.
These are called noninvasive BCIs.
Other systems place electrodes closer to brain tissue through an implanted device.
These are called implantable BCIs.
A simple comparison is:
Noninvasive BCI → Sensors outside the head
Implantable BCI → Sensors placed within or near neural tissue
Implanted systems may be able to obtain more detailed signals for certain applications, but they also involve greater medical, technical, and safety considerations.
What Could BCIs Be Used For?
One of the most important current areas of BCI development involves helping people whose ability to move or communicate has been impaired.
Potential applications include helping a person:
move a computer cursor;
type or select words;
communicate through a computer;
control a prosthetic limb;
operate a robotic or assistive device;
interact with a wheelchair or mobility system;
participate in rehabilitation;
or receive certain forms of sensory feedback.
For example:
Person Intends to Move Prosthetic Hand → BCI Detects Neural Signals → Computer Interprets Signals → Prosthetic Hand Moves
In this example, the technology is creating a new pathway between the person’s intended action and an external device.
Can Information Travel the Other Direction?
Some neural technologies do more than detect signals.
They may also deliver carefully controlled electrical stimulation to parts of the nervous system.
This means that some systems can potentially operate in both directions:
Brain → Technology
and
Technology → Controlled Neural Stimulation
This is sometimes called a bidirectional interface.
A familiar comparison is a conversation.
One person speaks and another listens, but then the direction reverses.
A bidirectional neural interface similarly allows limited information to move in both directions, although the signals involved are highly specialized and technologically constrained.
It does not mean a computer can freely place thoughts, memories, or ideas into a person’s mind.
Where Artificial Intelligence Fits In
Brain signals can be complicated.
A BCI may collect large amounts of electrical information that would be difficult to interpret manually.
This is where artificial intelligence and artificial neural networks may become useful.
The BCI collects the signals.
The artificial intelligence helps identify patterns within those signals.
The computer then uses those interpreted patterns to perform a defined action.
For example:
Brain Signal → BCI Detects Signal → AI Recognizes Pattern → Computer Identifies Intended Command → Device Responds
Artificial intelligence is therefore often the interpreter, while the BCI is the interface.
A Helpful Everyday Comparison
A smartphone provides a useful analogy.
When you speak to a voice assistant:
Your Voice → Microphone → Software Analysis → Command → Phone Responds
The microphone does not understand your words.
It collects the sound.
Software processes that information and determines what command may have been given.
A BCI can operate according to a somewhat similar principle:
Brain Activity → Neural Sensor → Software Analysis → Command → Device Responds
The signals and technology are very different, but the general relationship is easier to understand this way.
The sensor gathers information, the software interprets it, and the device performs an action.
Important Limitations
BCIs can be impressive without possessing unlimited abilities.
Detecting neural activity does not automatically mean:
reading every thought
understanding consciousness
knowing everything a person intends
accessing every memory
or
controlling the entire brain
A BCI is designed around particular measurable signals and particular intended functions.
Likewise, artificial intelligence analyzing those signals does not become the person’s mind or consciousness.
It remains an engineered computational system processing information.
Privacy, Security, and Human Control
BCIs can generate unusually sensitive information because they interact with neural activity.
That makes privacy, cybersecurity, user control, and appropriate oversight especially important.
Questions include:
Who can access the neural data?
Where is the data stored?
Can the user control when the device is operating?
Can information be transmitted without authorization?
How is the system protected against hacking?
What happens if the software makes a mistake?
Can the device be disabled or removed where appropriate?
Who controls updates to the system?
What information is actually being collected?
How much control remains with the person using the technology?
These questions become increasingly important as the technology becomes more capable.
The Person Should Remain More Important Than the Technology
The purpose of a BCI should not simply be to create the closest possible connection between a person and a computer.
The more important question is:
What legitimate benefit does this technology provide to the person, and is that benefit proportionate to its risks and consequences?
A BCI may provide extraordinary benefits when it helps someone communicate, regain functional capability, control an assistive device, or overcome a serious limitation.
But greater technological integration is not automatically better merely because it is possible.
The person should remain the beneficiary and responsible participant, rather than being treated merely as a collection of brain signals or another device connected to a network.
In Summary
The simplest way to understand the terminology is:
Artificial Neural Network = Software that analyzes information
Biochip = Technology that senses or interacts with biological information
Brain–Computer Interface = Technology that connects measurable brain activity with a computer or device
These technologies can work together.
For example:
Brain → BCI → Artificial Intelligence → Computer → Device
And if that computer is connected to the internet:
Brain → BCI → Computer → Internet
That is what people generally mean when discussing technology that could someday create increasingly direct connections between human neural activity and connected digital systems.
The important distinction is that the BCI creates the interface with the brain, while artificial neural networks or other software may help interpret the information coming from that interface.
Materials & Technologies Enabling Biointegrated Systems
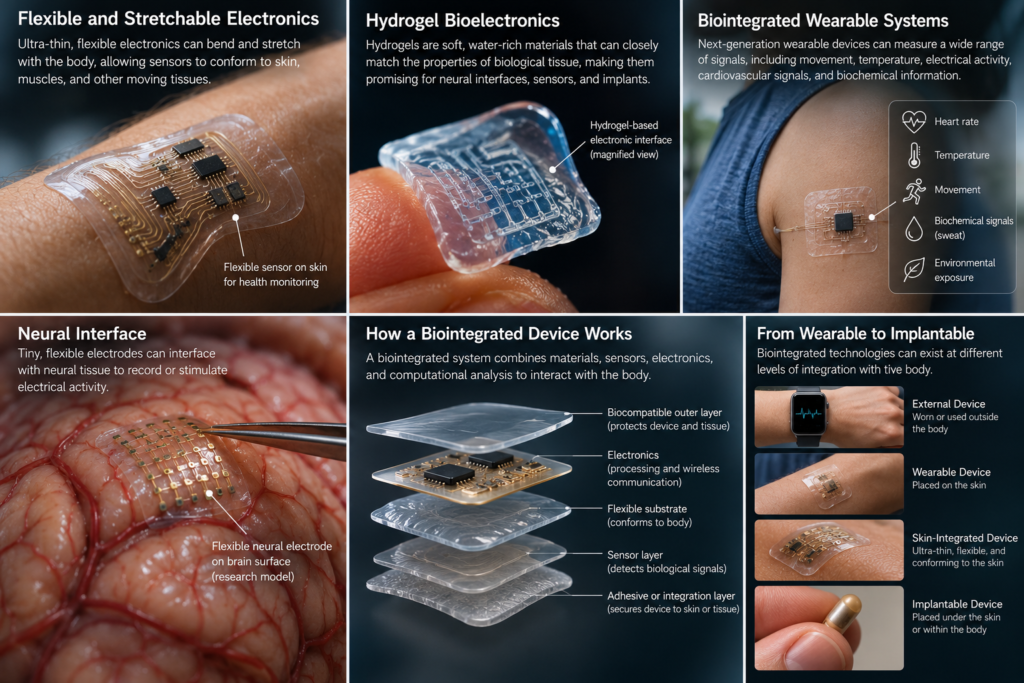
Creating technologies that can operate closely with the human body presents a basic engineering challenge: the human body is soft, curved, wet, moving, and biologically active, while conventional electronics are often rigid, flat, and comparatively inflexible.
Research in biointegrated electronics therefore focuses not only on making devices smaller, but also on developing materials and designs that can interact with the body more safely, comfortably, reliably, and effectively.
Flexible and Stretchable Electronics
Conventional electronic components are generally designed for rigid surfaces. Human skin, organs, muscles, and other tissues continually bend, stretch, and move.
Flexible and stretchable electronics are designed to accommodate this movement.
These technologies can allow sensors and electronic systems to conform more closely to areas such as:
skin;
muscles;
the heart;
neural tissue;
and other curved or moving biological surfaces.
This can improve the quality of the interface between the electronic device and the biological system while reducing some of the mechanical limitations associated with rigid electronics.
Research by Kim, Ghaffari, Lu, and Rogers examined flexible and stretchable electronic systems capable of integrating with the soft and dynamic surfaces of the human body, including applications involving the skin, heart, and brain.
Read the article — Flexible and Stretchable Electronics for Biointegrated Devices
Hydrogel Bioelectronics
Another important area of research involves hydrogels.
Hydrogels are water-rich materials whose softness and mechanical characteristics can resemble certain biological tissues more closely than traditional rigid electronic materials.
This makes them potentially useful as interfaces between electronic systems and the body.
Researchers have explored hydrogel-based technologies for applications involving:
biological sensing;
neural recording;
electrical stimulation;
wearable devices;
implantable devices;
diagnostics;
and other forms of bioelectronic interaction.
A major engineering objective is to create an interface that can maintain useful electrical communication while remaining compatible with soft biological tissue.
Yuk, Lu, and Zhao reviewed the development of hydrogel bioelectronics and examined how hydrogels may help address the mechanical and functional differences between living tissue and conventional electronic systems.
Read the article — Hydrogel Bioelectronics
Biointegrated Wearable Systems
Not every technology interacting closely with the body must be implanted.
Biointegrated wearable systems can place sensors directly against or very near the skin in forms designed to move naturally with the body.
Depending upon their design, these systems may measure:
movement;
temperature;
electrical activity;
cardiovascular signals;
sweat and other biochemical information;
environmental exposure;
or other relevant physiological conditions.
Unlike conventional rigid wearable devices, some biointegrated systems are designed to behave more like thin patches or flexible layers that conform closely to the body’s surface.
Ray and colleagues reviewed developments in these technologies, including sensing platforms, materials, power systems, and data-processing approaches for measuring biophysical, biochemical, and environmental signals.
Read the article — Bio-Integrated Wearable Systems: A Comprehensive Review
Why the Physical Interface Matters
For increasingly integrated human–machine systems, the computational technology is only part of the engineering problem.
A system must also be able to obtain meaningful information from the body—or deliver an appropriately controlled signal to it—through a physical interface.
Conceptually:
Human Body → Physical Interface → Sensor or Electrode → Electronics → Computational System
For some applications, the process may also operate in the opposite direction:
Computational System → Electronics → Controlled Stimulation → Biological Interface
The quality of the physical interface can affect signal quality, reliability, comfort, durability, safety, and the usefulness of the overall system.
This is why developments in materials science, flexible electronics, electrodes, hydrogels, sensors, and biocompatible interfaces are important to technologies such as wearable health monitors, implanted medical devices, prosthetics, and brain–computer interfaces.
From Wearable to Implantable
Human–technology interfaces can exist at different levels of physical integration.
Conceptually:
External Device → Wearable Device → Skin-Integrated Device → Implantable Device → Neural or Tissue Interface
Moving further toward direct biological integration can potentially provide access to different or more detailed signals.
However, closer physical integration can also introduce additional considerations involving:
safety;
biocompatibility;
surgical risk;
infection;
durability;
reliability;
maintenance;
device removal or replacement;
privacy and security;
and long-term effects.
Greater physical integration should therefore not automatically be assumed to be superior.
The appropriate level of integration depends upon the purpose of the technology and whether the expected benefit reasonably justifies the additional complexity and risk.
In Summary
The development of increasingly integrated human–machine systems depends not only upon artificial intelligence, software, or connectivity, but also upon the physical interface between technology and the human body.
Flexible electronics can conform to moving biological surfaces.
Hydrogels may provide softer interfaces between electronics and living tissue.
Biointegrated wearable systems can place sophisticated sensing technologies directly against the body without requiring implantation.
Together with sensors, electrodes, implantable devices, and computational systems, these technologies are helping expand the range of ways in which biological information can be measured and used.
The objective, however, should not simply be to place technology increasingly close to or within the human body. The appropriate degree of integration depends upon the legitimate purpose, demonstrated benefit, available evidence, safety, reliability, proportionality, and effects upon the person and surrounding system.
Risks vs. Benefits

The potential use of technologies such as biochips, neural implants, and brain–computer interfaces (BCIs) in otherwise healthy individuals is an area of growing technological interest and ethical discussion.
Unlike therapeutic applications intended to restore lost function, treat disease, or compensate for disability, implantation in healthy individuals may be pursued for purposes such as monitoring, convenience, communication, performance enhancement, expanded interaction with digital systems, or other forms of human–technology integration.
Whether such technologies become more widely adopted will likely depend upon factors including their demonstrated benefits, medical and technological risks, long-term safety, reliability, reversibility, respect for bodily integrity, privacy and cybersecurity implications, regulatory requirements, ethical considerations, effects upon human agency, and informed individual choice.
Technological capability alone does not establish that implantation is necessary or beneficial.
The relevant question is whether a particular application provides a legitimate and proportionate benefit relative to its risks, limitations, alternatives, effects upon bodily integrity, and broader consequences for the person.
Cybersecurity Risks in Connected Medical Implants

The increasing use of wireless communication and remote-monitoring capabilities in medical implants has expanded opportunities for patient monitoring, device management, and clinical care.
At the same time, increased connectivity can introduce cybersecurity vulnerabilities that must be considered alongside the medical benefits of the technology.
An implantable medical device that communicates wirelessly with an external receiver, smartphone, clinical monitoring system, or other networked infrastructure may create potential pathways for unauthorized access, interception, manipulation, disruption, or misuse if appropriate safeguards are not maintained.
Cybersecurity is therefore not merely an information-technology issue in this context. For certain medical devices, a cybersecurity failure could potentially affect:
patient privacy;
confidentiality of medical information;
device availability;
reliability of monitoring;
integrity of transmitted data;
clinical decision-making;
device operation;
and, in some circumstances, patient safety.
The following publications provide useful research and technical background concerning these risks.
1. Are Implanted Electronic Devices Hackable?
Alexander, Haseeb, and Baranchuk (2019) review cybersecurity concerns associated with implanted cardiac electronic devices, including pacemakers and implantable cardioverter-defibrillators.
The authors discuss how wireless connectivity and remote monitoring have created new capabilities while also introducing potential cybersecurity vulnerabilities. They also examine responses by manufacturers, clinicians, regulators, and professional organizations to identified security concerns.
Read the article — Are Implanted Electronic Devices Hackable?
2. Investigating the Security Threats on Networked Medical Devices
Zaldivar, Tawalbeh, and Muheidat (2020) examine cybersecurity threats affecting networked medical devices, including technologies such as pacemakers and insulin pumps.
Their work considers vulnerabilities associated with connected healthcare systems and emphasizes the need to address security throughout the design, deployment, and operation of network-capable medical devices.
Read the article — Investigating the Security Threats on Networked Medical Devices
3. Cybersecurity in Healthcare: A Narrative Review of Trends, Threats and Ways Forward
Coventry and Branley (2018) provide a broader review of cybersecurity risks across healthcare.
The paper discusses how increasing connectivity has exposed healthcare infrastructure, electronic records, and medical devices to additional vulnerabilities and emphasizes that cybersecurity can affect not only information privacy but also patient trust and safety.
4. Securing Wireless Implantable Devices for Healthcare: Ideas and Challenges
Malasri and Wang (2009) examine the security challenges associated specifically with wireless implantable medical devices.
The authors discuss threats such as unauthorized interception of wireless communications, tracking, device impersonation, and malicious commands. They also examine an important engineering challenge: implantable devices typically operate with significant limitations involving battery power, processing capacity, memory, and communication resources.
These constraints can make conventional cybersecurity approaches more difficult to implement.
Read the article — Securing Wireless Implantable Devices for Healthcare: Ideas and Challenges
5. Security Tradeoffs in Cyber Physical Systems: A Case Study Survey on Implantable Medical Devices
Altawy and Youssef (2016) examine implantable medical devices as cyber-physical systems, where cybersecurity decisions can have consequences in the physical world.
Their analysis highlights the relationship among:
security;
safety;
availability;
authorized access;
emergency access;
and Resource limitations.
A particularly important challenge is that strong access restrictions may protect a device from unauthorized use while potentially creating difficulties when legitimate emergency access is required.
Cybersecurity design must therefore consider not only how to block unauthorized access, but also how to preserve appropriate availability and patient safety.
Cybersecurity Requires Whole-System Thinking
Connected medical implants do not operate by themselves.
A typical system may involve:
Implanted Device → Wireless Communication → External Receiver or Smartphone → Software → Network Infrastructure → Clinical Platform → Healthcare Provider
A vulnerability at any point in this larger system may affect the security or reliability of the overall configuration.
Cybersecurity analysis should therefore consider not only the implanted device, but also:
wireless protocols;
external receivers;
smartphones or communicators;
authentication systems;
software;
cloud or server infrastructure;
clinical networks;
software updates;
user access;
data storage;
and the procedures used by healthcare organizations and device manufacturers.
Security, Safety, and Accessibility Must Be Balanced
Medical-device cybersecurity presents an unusual engineering challenge because maximum restriction is not automatically the safest configuration.
A device may need strong protection against unauthorized access while still allowing appropriate communication, clinical monitoring, maintenance, software updates, or emergency intervention.
Conceptually:
Security + Safety + Appropriate Availability + Reliability → Responsible Device Operation
Cybersecurity measures should therefore protect the system without unnecessarily preventing legitimate clinical use.
In Summary
Wireless and networked medical implants can provide significant benefits through remote monitoring, communication, device management, and more responsive clinical care.
However, increased connectivity also creates additional cybersecurity responsibilities.
Potential risks can involve unauthorized access, interception of sensitive information, manipulation of communications, disruption of device availability, or interference with system operation.
Protecting connected medical implants therefore requires coordinated attention from manufacturers, healthcare providers, cybersecurity professionals, regulators, software developers, and users throughout the device life cycle.
The objective is not simply to maximize connectivity or security in isolation, but to develop systems in which cybersecurity, privacy, reliability, appropriate access, clinical usefulness, and patient safety are considered together as part of the complete System of Interest.
The Risk of Medical Device Hijacking

As medical implants and their supporting systems become increasingly connected, one cybersecurity concern is the possibility of unauthorized access or control.
In plain language, this type of event may sometimes be described as “hijacking” a medical device.
Within this context, hijacking refers specifically to a situation in which an unauthorized party gains enough access to interfere with, alter, or control some aspect of a connected medical device or its supporting system.
It is useful, however, to distinguish device hijacking from other cybersecurity incidents such as data theft, interception, or denial of service.
Unauthorized Device Control
The most direct form of medical-device hijacking would involve an unauthorized party attempting to alter the operation or configuration of a connected device.
Depending upon the device, this could potentially involve changes to:
operating settings;
programmed parameters;
communication functions;
alerts;
device commands;
or other controllable functions.
For medically important devices such as pacemakers, insulin-delivery systems, neurostimulators, or other connected technologies, unauthorized manipulation could create serious safety concerns.
This does not mean that every connected implant is easily accessible or remotely controllable.
Actual risk depends upon the particular device, its architecture, communication methods, security controls, software, supporting infrastructure, and known vulnerabilities.
Unauthorized Access to Medical Data
A connected medical system may also be targeted for the information it collects or transmits.
Potentially sensitive information can include:
health measurements;
device status;
patient identifiers;
treatment information;
usage history;
or other medical data.
Unauthorized access to this information represents a data-security and privacy breach, even when the attacker does not gain control of the medical device itself.
Accordingly:
Unauthorized Data Access ≠ Automatically Device Hijacking
Both are serious cybersecurity concerns, but they involve different forms of system compromise.
Disruption and Denial of Service
Another risk is denial of service, in which legitimate access to a device or supporting system is disrupted or made unavailable.
For example, a cybersecurity incident could potentially interfere with communication between:
Implanted Device → External Receiver → Network → Clinical Monitoring System
A denial-of-service event does not necessarily mean that an attacker has taken control of the implant.
Instead, the attack may prevent legitimate communication, monitoring, or system availability.
For medical technologies, loss of availability can itself become important because healthcare professionals or patients may depend upon timely access to device information or functions.
Cybersecurity Protection Requires Multiple Layers
Protecting connected medical implants requires more than a single security feature.
Appropriate safeguards may include:
strong authentication;
encryption of sensitive communications;
secure communication protocols;
access controls;
secure software and firmware updates;
vulnerability monitoring;
appropriate software maintenance;
logging and anomaly detection;
protected clinical infrastructure;
device-specific risk management;
and procedures for responding to newly discovered vulnerabilities.
The security of the implant also depends upon the security of the larger system around it.
Conceptually:
Implant → Communicator / Smartphone → Network → Software → Clinical Platform → Healthcare Provider
A weakness at one point in this chain can potentially affect the larger system.
Security Must Also Preserve Legitimate Access
Connected medical devices present an important engineering challenge.
Strong security is necessary, but the device may also need to remain available for:
legitimate monitoring;
maintenance;
clinical programming;
software updates;
troubleshooting;
and emergency care.
The objective is therefore not simply to make the device as inaccessible as possible.
The objective is to create a system that appropriately balances:
Cybersecurity + Patient Safety + Reliability + Authorized Access + Clinical Availability
Shared Responsibility
Medical-device cybersecurity depends upon multiple participants.
These may include:
device manufacturers;
software developers;
healthcare providers;
hospital and clinical IT teams;
cybersecurity professionals;
regulators;
patients and caregivers;
and other parties involved in maintaining the connected system.
Manufacturers may need to identify and correct vulnerabilities.
Healthcare organizations may need to protect networks and clinical infrastructure.
Software developers may need to maintain secure applications and update mechanisms.
Patients and caregivers may also need to follow device-specific guidance concerning updates, passwords, connectivity, and authorized accessories.
In Summary
The term medical-device hijacking can appropriately describe a scenario in which an unauthorized party gains control over or materially interferes with the operation of a connected medical device.
However, it should not be used as a catch-all term for every cybersecurity problem.
Connected medical systems may face several distinct categories of risk:
Unauthorized Control → Device Manipulation
Unauthorized Data Access → Privacy or Data Breach
Denial of Service → Loss or Disruption of Legitimate Availability
These risks can sometimes overlap, but they should remain analytically distinguishable.
Addressing them requires a whole-system cybersecurity approach that protects device operation, patient information, authorized access, system availability, privacy, reliability, and patient safety throughout the life cycle of the technology.
Compromising the Person Through Connected Systems

The idea of “hijacking” can extend beyond unauthorized control of a medical implant, but the term should be used carefully.
A person cannot ordinarily be hijacked in the same technical sense as a computer or device. However, malicious actors can use technology to compromise or manipulate important parts of a person’s connected life, including identity, information, accounts, decision-making, digital environments, connected devices, and—in emerging neural systems—sensitive neural data and device functions.
In some cases, an attacker targets the technology.
In others, the attacker targets the person through deception, impersonation, psychological manipulation, coercion, or misuse of information.
As technology becomes more deeply integrated with the human body and nervous system, the distinction between compromising technology around a person and compromising a technological interface connected to the person becomes increasingly important.
1. Digital Identity Theft
A malicious actor may steal enough personal information to impersonate another person online.
Compromised information may include:
account credentials;
financial information;
identifying information;
authentication data;
personal communications;
or access to other sensitive digital systems.
The attacker may then attempt to access accounts, make unauthorized transactions, impersonate the individual, obtain additional information, or use the stolen identity in further attacks.
In this sense, the attacker is not taking control of the person but may be attempting to take control of part of the person’s digital identity, access, or authority.
2. Social Engineering
Not every cyberattack begins by defeating a computer.
Sometimes the attacker attempts to defeat the human decision-making process surrounding the computer.
Social engineering uses deception, impersonation, urgency, fear, trust, curiosity, authority, or other pressures to persuade someone to perform an action that benefits the attacker.
Examples may include:
phishing;
spear-phishing;
fraudulent messages;
impersonation;
pretexting;
baiting;
false technical-support requests;
deceptive login pages;
or fraudulent requests for money, credentials, or access.
The objective may be to persuade the person to voluntarily provide access that the attacker could not easily obtain through technical means alone.
Accordingly:
A Technically Secure System Can Still Be Compromised Through a Deceived User
3. Psychological and Informational Manipulation
Technology can also be used to influence what people believe, notice, fear, prioritize, or choose.
Misinformation, selectively presented information, manipulative advertising, propaganda, fraudulent content, or coordinated influence campaigns may attempt to exploit:
fear;
anger;
urgency;
confirmation bias;
social pressure;
familiarity;
trust;
emotional vulnerability;
or other predictable features of human decision-making.
This does not mean that exposure automatically controls a person’s behavior.
People remain capable of judgment, reflection, verification, resistance, and responsible choice.
However, deliberately engineered information environments may influence decisions, particularly when deceptive material is repeated, emotionally charged, highly personalized, or presented as coming from a trusted Source.
The concern is therefore influence and manipulation, not automatic control of the person.
4. Deepfakes and Digital Impersonation
Artificial intelligence can be used to create increasingly convincing synthetic:
voices;
images;
videos;
documents;
messages;
and other digital content.
A malicious actor may use these technologies to make it appear that a real person said or did something that never occurred.
Potential uses include:
impersonation;
fraud;
fabricated evidence;
reputational attacks;
deceptive communications;
extortion;
or attempts to manipulate other people into taking action.
Deepfakes therefore create not only a cybersecurity problem but also a Source-authentication problem.
Seeing or hearing something that appears authentic does not automatically establish that it actually originated from the person being represented.
Accordingly:
Apparent Authenticity ≠ Automatically Genuine Origin
5. Ransomware and System Extortion
Ransomware targets computers, networks, or data rather than directly taking control of a person.
An attacker may use malicious software to encrypt, disable, or otherwise deny access to important systems or information and then demand payment or another concession.
This can create substantial leverage when access to:
business systems;
personal records;
communications;
medical information;
financial information;
or essential services
becomes unavailable.
The attacker is therefore attempting to gain control over something the victim depends upon, thereby creating pressure on the person or organization.
6. Exploitation of Smart Homes and Connected Environments
Modern homes, vehicles, workplaces, and personal environments may contain numerous connected devices.
Examples include:
cameras;
door locks;
thermostats;
speakers;
lighting;
appliances;
vehicles;
security systems;
wearable devices;
medical devices;
and other Internet of Things technologies.
If these systems are poorly secured, unauthorized access could potentially allow an attacker to:
observe private information;
surveil occupants;
manipulate device operation;
interfere with environmental controls;
compromise physical access;
disrupt services;
or otherwise affect the person’s surroundings.
This illustrates an important distinction:
The Person May Not Be Technically Compromised Even Though the Technology Surrounding the Person Is
As physical environments become increasingly connected, cybersecurity can affect not only information but also the conditions and systems upon which people rely.
7. Brain–Computer Interfaces and Neural-System Exploitation
Brain–computer interfaces (BCIs) introduce a more direct category of concern because they create an engineered interface between measurable neural activity and technological systems.
As discussed previously, a BCI may detect neural signals and translate them into defined commands for computers, communication systems, prosthetic devices, robotic equipment, or other technologies.
This creates an important cybersecurity boundary.
If a BCI or one of its supporting systems were compromised, an attacker could potentially target:
neural-signal data;
communication between the implant and an external device;
signal-processing software;
user permissions;
decoded commands;
connected devices;
system settings;
or other functions supported by the particular BCI.
Conceptually:
Brain → BCI → Signal Processing → Computer → Connected Device
An attacker would not necessarily need to control the person’s mind to cause harm.
Compromising one part of that technological pathway could potentially cause the system’s Output to differ from what the person intended.
For example:
Person Intends Action → BCI Detects Signal → Compromised System Alters Command → External Device Performs Different Action
This would represent hijacking of the technological interface or connected system, not necessarily hijacking of the person.
Could Someone Literally Hijack a Person Through a BCI?
This question becomes especially important as neural interfaces become more sophisticated.
Current BCIs should not be understood as providing unrestricted technological access to a person’s entire mind.
A BCI may detect particular measurable neural signals and associate them with defined functions.
That does not automatically provide access to:
every thought;
every memory;
consciousness;
identity;
moral judgment;
personality;
the will;
or complete control of the body.
Accordingly:
BCI Hijacking ≠ Automatically Hijacking the Entire Person
The more accurate present concern is that an attacker might compromise the technological interface between the person and connected systems.
Neural Data Could Become an Increasingly Sensitive Target
BCIs can produce information derived from neural activity.
As these systems become more capable, the sensitivity and informational value of that data may increase.
Potential targets could include:
recorded neural signals;
decoded movement intentions;
communication-related signals;
device-use patterns;
associated health information;
or other data inferred from the BCI system.
This creates an important distinction:
Access to Neural Data ≠ Complete Access to the Mind
A computational system may infer specific information from measurable neural activity without possessing complete knowledge of what the person thinks, believes, remembers, intends, or experiences.
Future Bidirectional BCIs May Create Greater Risks
Some neural-interface technologies may not only record neural activity but may also provide controlled electrical or other stimulation to neural tissue.
This creates a potentially bidirectional pathway:
Brain → Technology
and
Technology → Neural Stimulation
If future systems combine increasingly sophisticated neural recording with increasingly sophisticated stimulation, the cybersecurity consequences of unauthorized access could become more significant.
Potential risks could include unauthorized:
stimulation;
alteration of intended sensory feedback;
disruption of therapeutic functions;
interference with device-mediated perception;
manipulation of device-generated signals;
or other neurological effects within the capabilities of the particular system.
These possibilities deserve serious cybersecurity consideration.
However, even a compromised bidirectional BCI should not automatically be described as giving an attacker unrestricted control over the entire human person.
The possible effect would remain constrained by:
where the interface is located;
which neural signals it can detect;
which neural structures it can stimulate;
the type and intensity of stimulation;
the software and hardware architecture;
biological variability;
safety limits;
and the actual capabilities engineered into the system.
Accordingly:
Neural Influence ≠ Automatically Total Human Control
The Distinction Between Influence, Interference, and Control
As technology becomes increasingly integrated with the person, it is useful to distinguish several levels of concern.
Digital Manipulation → Attempts to Influence Decisions
Environmental Compromise → Control of Connected Systems Around the Person
Device Hijacking → Unauthorized Control of a Device Used by the Person
BCI Compromise → Unauthorized Interference With a Neural-Technological Interface
Neural Influence → Potential Effects Produced Through a Neural Interface
These conditions should not automatically be collapsed into:
Total Control of the Human Person
The distinction matters because responsible analysis should neither minimize genuine technological risks nor attribute capabilities to technology that have not been established.
Greater Integration Creates Greater Security Responsibility
The closer a technological system operates to the human body, nervous system, or essential functioning, the more consequential a cybersecurity failure may become.
A compromised social-media account may expose personal information.
A compromised smart-home system may affect the person’s environment.
A compromised medical implant may affect bodily functioning.
A compromised neural interface could potentially affect sensitive neural data or functions mediated by the interface.
Conceptually:
Greater Technological Access to the Person → Greater Need for Security, Privacy, Control, and Oversight
This does not mean that greater integration is inherently wrong or unsafe.
It means that the required level of protection should increase with the potential consequence of unauthorized access.
Protecting the Person Requires More Than Device Security
Safeguards may include:
strong authentication;
multi-factor authentication where appropriate;
secure software and firmware;
encrypted communications;
protected neural data;
verified software updates;
strict access controls;
secure external devices;
monitoring for unauthorized activity;
independent verification of consequential communications;
protection against phishing and impersonation;
user-controlled permissions;
safeguards against unauthorized stimulation where applicable;
and safe recovery, disabling, or shutdown mechanisms where technically appropriate.
Security should extend beyond the implant itself to the entire connected architecture.
For example:
Person → Implant / BCI → External Device → Software → Network → Cloud Infrastructure → Connected System
Every interface may introduce its own security requirements.
Human Judgment Remains an Important Safeguard
Many attempts to compromise a person do not begin with highly advanced technology.
They begin with a deceptive message, false Source, fraudulent request, manipulated image, or emotional pressure.
Before acting upon consequential information, a person can ask:
Who is the actual Source?
Can the Source be independently verified?
What evidence supports the claim?
Is someone creating unnecessary urgency or pressure?
Am I being asked to surrender information, access, money, authority, or control?
Does another reliable channel confirm what I am being told?
Cybersecurity is therefore partly a technical discipline and partly a discipline of Source evaluation, verification, Gateway Guarding, and responsible choice.
The Person Is More Than the Connected System
As technology becomes increasingly integrated with biological and neural systems, one distinction should remain fundamental:
The technological interface is associated with the person. It is not the totality of the person.
A person should not be reduced to:
neural signals;
biological measurements;
data;
software Outputs;
device configurations;
connected accounts;
or networked components.
Protecting connected technology should therefore serve the broader objective of protecting the person who uses or depends upon it.
In Summary
Malicious actors can attempt to compromise important parts of a person’s connected life through:
Identity → Impersonation
Accounts → Unauthorized Access
Information → Manipulation or Deception
Data → Theft or Exposure
Computer Systems → Ransomware or Disruption
Connected Environments → Unauthorized Device Control
Medical Devices → Potential Interference With Bodily Functions
Brain–Computer Interfaces → Potential Interference With Neural Data, Commands, or Device Functions
As neural interfaces become more capable, the potential consequences of unauthorized access may become increasingly serious.
However:
Compromising a BCI Does Not Automatically Mean Taking Complete Control of the Human Person
The responsible approach is neither to dismiss the potential risk nor to assume technological capabilities that have not been established.
The objective should be to recognize that increasingly intimate human–technology integration creates increasingly important cybersecurity boundaries, requiring proportionately strong protection of privacy, bodily integrity, neural data, human agency, authorized control, safety, security, and responsible choice.
Protecting Bio-IoT and Connected Medical Devices

Reducing the risk that bio-IoT devices, connected medical implants, and their supporting systems are hacked, manipulated, or accessed without authorization requires security throughout the entire system life cycle.
No single safeguard can eliminate cybersecurity risk. Effective protection generally depends upon multiple layers of security working together across the device, software, communications, network infrastructure, healthcare environment, and authorized users.
1. Strong and Appropriate Authentication
Connected systems should use authentication methods appropriate to the sensitivity and risk of the particular device or function.
Depending upon the system, this may include:
strong passwords or credentials;
multi-factor authentication;
cryptographic device authentication;
biometric authentication where appropriate;
or other methods for verifying authorized users, devices, and systems.
The objective is to prevent unauthorized parties from gaining access while preserving appropriate access for legitimate users and healthcare professionals.
2. Secure Communications
Information exchanged between an implanted or wearable device and external systems should be protected against unauthorized interception, alteration, or impersonation.
Appropriate protections may include:
encrypted communications;
authenticated connections;
secure communication protocols;
protection against replay or impersonation attacks;
and verification that communicating devices or systems are authorized.
The specific security approach should be appropriate to the device architecture, clinical use, and associated risks.
3. Secure and Verified Software Updates
Connected medical technologies may require software or firmware updates during their operational life.
Updates should be delivered through authorized, authenticated, and appropriately validated mechanisms.
A secure update process should help ensure that:
the update comes from a trusted Source;
the software has not been altered;
only authorized updates can be installed;
relevant risks have been evaluated;
and the device can continue operating safely after the update.
The objective is not simply to install the newest software available, but to maintain the system securely and appropriately throughout its life cycle.
4. Access Controls and Least Privilege
Users, applications, devices, and services should receive only the access necessary to perform their legitimate functions.
For example, a system may distinguish between permissions for:
patients;
caregivers;
clinicians;
technicians;
manufacturers;
software services;
and administrative personnel.
Limiting unnecessary privileges can reduce the consequences of a compromised account, device, or application.
5. Protection Against Physical Tampering
Where appropriate to the device, physical protections can help reduce unauthorized modification or access.
These may include:
tamper-resistant components;
protected diagnostic interfaces;
secure enclosures;
controlled maintenance access;
or mechanisms that detect unauthorized physical modification.
Physical-security requirements will vary substantially depending upon whether the technology is implanted, wearable, externally connected, or part of supporting infrastructure.
6. Protection of Sensitive Data
Sensitive medical, biological, personal, and device information should be protected both while stored and while transmitted.
Appropriate data protection may include encryption, access controls, authentication, secure storage, and limitations on unnecessary collection or retention.
This is especially important because connected health technologies may generate information concerning:
medical conditions;
physiological measurements;
device operation;
treatment;
identity;
activity;
and potentially other highly sensitive aspects of a person’s life.
7. Secure Boot and Software Integrity
Where technically appropriate, connected devices can use mechanisms that verify software before it is allowed to execute.
A secure boot process can help prevent unauthorized or altered firmware from being loaded onto a device.
Additional integrity controls may help verify that critical software, configuration data, and executable components remain authentic and have not been improperly modified.
8. Monitoring, Logging, and Anomaly Detection
Connected medical systems should, where appropriate and technically feasible, provide mechanisms for identifying unusual or potentially unauthorized activity.
These may include:
security logging;
event monitoring;
anomaly detection;
alerts;
device-status monitoring;
and procedures for investigating suspected cybersecurity events.
Not every implant can perform extensive monitoring itself because power, processing, memory, communications, and clinical requirements may impose significant limitations.
Monitoring may therefore occur across the larger connected system, including external communicators, applications, clinical platforms, networks, or manufacturer infrastructure.
9. Secure Development Throughout the Life Cycle
Cybersecurity should be considered from the beginning of product development rather than added only after a device has been created.
Secure development practices may include:
threat modeling;
secure coding;
security testing;
vulnerability assessment;
penetration testing where appropriate;
software-component management;
risk analysis;
verification and validation;
and post-market vulnerability management.
Security should continue to be evaluated as the device, software, threat environment, and supporting infrastructure change over time.
10. User Education and Awareness
Users also participate in the security of connected systems.
Patients, caregivers, clinicians, and other authorized users should receive understandable information about relevant security practices.
This may include guidance concerning:
passwords and authentication;
approved applications and accessories;
software updates;
phishing and impersonation attempts;
suspicious communications;
reporting unusual device behavior;
and appropriate responses to security notifications.
The user should not bear sole responsibility for cybersecurity, but informed use can strengthen the security of the overall system.
11. Manufacturer and Vendor Responsibility
Manufacturers and technology providers have an important responsibility to design products that can be securely deployed, maintained, updated, and supported throughout their expected life cycle.
Relevant considerations include:
secure design;
vulnerability disclosure processes;
timely evaluation of discovered vulnerabilities;
authenticated security updates;
transparent communication concerning significant risks;
continuing security support;
and planning for eventual end-of-support or device retirement.
Organizations selecting connected technologies should consider not only the capabilities of the product but also the quality and duration of the manufacturer’s cybersecurity support.
12. Resilience and Recovery
Security systems should also consider what happens after something goes wrong.
Where appropriate, connected medical technologies should be designed so that failures, cyber incidents, communication loss, or compromised components do not unnecessarily produce catastrophic consequences.
Resilience may include:
safe operating states;
recovery procedures;
backup capabilities;
protected configurations;
restoration mechanisms;
and continued essential function where reasonably possible.
The objective is not only to prevent attacks, but also to reduce harm and restore safe operation when prevention is insufficient.
Cybersecurity Is a Whole-System Function
A connected implant does not operate alone.
Its larger system may include:
Implant → External Communicator → Smartphone or Receiver → Software → Network → Cloud or Server Infrastructure → Clinical Platform → Healthcare Provider
Cybersecurity weaknesses can potentially arise at any point in this chain.
Protecting the implant therefore requires protection of the entire connected System of Interest, including the relationships and interfaces among its components.
Security Should Protect the Person
The ultimate objective of medical-device cybersecurity is not simply to protect data or technology.
It is to help protect the person who depends upon the system.
Accordingly, cybersecurity should support:
Safety + Privacy + Security + Reliability + Appropriate Access + Human Agency
Strong cybersecurity should protect against unauthorized access without unnecessarily preventing legitimate medical monitoring, treatment, maintenance, or emergency care.
In Summary
Preventing the hacking or unauthorized manipulation of bio-IoT and connected medical technologies requires a layered, life-cycle approach to cybersecurity.
Important protections include strong authentication, secure communications, encryption, access controls, software integrity, secure updates, physical protection where appropriate, monitoring and logging, secure development, user awareness, manufacturer accountability, resilience, and recovery planning.
These safeguards cannot guarantee that a connected device will never be compromised.
They can, however, reduce vulnerabilities, limit opportunities for unauthorized access, reduce the consequences of cybersecurity incidents, and strengthen the protection of sensitive data and device operation.
As biological and digital technologies become increasingly interconnected, cybersecurity should remain an integral part of system design and operation rather than an optional feature added after deployment.
The objective is responsible technological integration in which security, privacy, safety, reliability, appropriate access, bodily integrity, and human agency are protected together throughout the life cycle of the system.